
Pigment Treatment
Nevus of Ito Treatment: 1064nm Q-Switched Nd:YAG Protocol, Equipment and Aftercare
Nevus of Ito is a benign patch of blue-grey to slate-brown pigment lying deep in the dermis, almost always over one shoulder. Standard nevus of ito treatment uses a 1064nm Q-switched Nd:YAG laser to shatter that dermal pigment across spaced sessions, letting the body clear the fragments over following weeks. Educational content for clinics and distributors, not medical advice.
What is nevus of Ito?
Nevus of Ito is dermal melanocytosis, the shoulder counterpart of nevus of Ota. Our clinical atlas puts it plainly: same features as nevus of Ota, but in the acromiodeltoid distribution. Reference texts, StatPearls among them, place it in the distribution of the posterior supraclavicular and lateral cutaneous brachial nerves, hence its appearance across the supraclavicular fossa, scapula, deltoid and upper arm. DermNet calls that the shoulder girdle.
The patch is flat, smooth and usually one-sided. Colour runs brown through blue to near-black, shifting with the light because the pigment sits below the surface. Season and sun make no difference. The cause is an increased population of dermal melanocytes packed with melanin in the upper and middle dermis, well below the epidermis where most cosmetic pigment lives. Creams and peels never reach that depth.
Rule out the look-alikes before you treat
A brown-grey patch on a shoulder is not automatically a nevus of Ito. Several lesions share the neighbourhood, and a few respond badly or must never be lasered. Triage guide below, from our disease atlas and DermNet.
| Lesion | Typical site | Colour and depth | Difference from nevus of Ito | 1064nm QS suitable? |
|---|---|---|---|---|
| Hori nevus (ABNOM) | Malar cheeks, temples | Blue-grey to brown, dermal | Bilateral, facial, adult onset | Yes; higher pigment risk on facial skin |
| Mongolian spot | Lumbosacral area, buttocks | Grey-blue, dermal | From birth, regresses in childhood | In theory; our atlas says it clears itself, so leave it |
| Becker nevus | Shoulder, scapula, upper chest | Light brown, epidermal, thickened | Coarse hair, textured; Ito is glabrous and flat | Poor, inconsistent, repigments |
| Cafe-au-lait macule | Anywhere, neck and shoulder | Even light brown, epidermal | From infancy, brown not blue-grey, sun-darkening | Demanding; our atlas wants high energy, short pulse width; relapse common |
| Congenital melanocytic nevus | Anywhere, shoulder included | Brown to black nevus cell nests | Palpable, often raised or hairy, from birth | No. Refer for assessment first |
| Post-inflammatory hyperpigmentation | Site of the earlier injury | Brown to black, epidermal basal melanin | Copies the earlier lesion's shape, sun-linked | Yes, though time and sun avoidance often suffice |
Refer for assessment or biopsy instead of treating when you see:
- A nodule, papule or firm area inside a supposedly flat patch.
- Ulceration, bleeding or itch in a lesion that never had symptoms.
- Rapid growth, or colour or border change in a long-stable patch.
- Coarse hair plus thickening, pointing to Becker nevus.
- Six or more cafe-au-lait macules, or other syndrome signs.
- Any lesion you aren't confident about. Uncertainty is the referral indication.
Melanoma inside dermal melanocytosis is rare, but transformation within a nevus of Ito is documented. Hence the list.
How a 1064nm Q-switched laser clears it
The governing principle is selective photothermolysis, published by Anderson and Parrish in 1983: pick a wavelength the target absorbs strongly, deliver it in a pulse shorter than the target's thermal relaxation time, and the target breaks up while neighbouring tissue stays cool. A Q-switched Nd:YAG does that in nanosecond pulses, so melanin granules expand violently and fracture into fragments phagocytes can clear through the lymphatics.
Wavelength choice is not arbitrary. Longer wavelengths scatter less in the epidermis and go deeper, and our device archive records that 1064nm is preferentially absorbed by black and blue chromophores, barely by red or green. The 532nm output on the same platform is the opposite tool: strong on red and brown, shallow. DermNet lists 1064nm Q-switched Nd:YAG alongside alexandrite and QS ruby, adding that picosecond devices may now be most effective.
Treatment protocol and what to expect
Clearance is gradual and staged. Nobody removes a nevus of Ito in one visit. Sessions sit weeks to months apart, because the immune system needs that time to carry away shattered pigment. How many? An honest "usually several, sometimes many" beats a number you can't guarantee. Recurrence belongs in the consent talk too: DermNet notes pigment can return after apparent clearance, occasionally darker.
| Aspect | What to expect |
|---|---|
| Wavelength | 1064nm Q-switched Nd:YAG, nanosecond pulse |
| Target | Dermal melanocytes, upper to middle dermis |
| Sessions | Usually several; darker lesions take more |
| Spacing | Weeks to a few months between passes |
| Endpoint | Transient whitening, then mild swelling |
| Downtime | Redness and light crusting over days |
| Outcome | Gradual fading; results vary by lesion and skin type |
One measurement point deserves care, because it's where equipment marketing goes wrong. Clinical effect tracks fluence in J/cm², not millijoules, and a millijoule figure means nothing without a spot diameter. Run it yourself: 200mJ through a 3mm spot is about 2.8 J/cm², the same 200mJ through a 2mm spot roughly 6.4 J/cm². Same energy, double the fluence. Our archive, as an internal engineering rule of thumb and not a literature consensus, advises against systems whose maximum single pulse at 1064nm sits below roughly 200mJ: weak clearance, longer course, more pain, more complications. Treat that as a floor on device capability, never a setting, since a machine capped near 200mJ reaches useful fluence only at a tiny spot.
Recommended Pmise equipment
Three Pmise Q-switched Nd:YAG models cover the usual buying positions. Figures come from each model's published specification; where a value isn't published, ask.
| Model | Wavelengths | Pulse width | Max single pulse at 1064nm | Spot | Frequency | Delivery and beam |
|---|---|---|---|---|---|---|
| Pmise QN-03 | 1064nm, 532nm | 6 to 8 ns | 400mJ (800mJ double-pulse, 1200mJ triple-pulse) | 1 to 4mm, 0.5mm steps | 1 to 5 Hz | Water and air cooled handpiece |
| Pmise QN-12 | 1064nm, 532nm | 8 ns | 800mJ | 2x2mm and 3x3mm square | 1 to 5 Hz | Top-hat homogeneous square beam |
| Pmise QE-01 | 1064nm, 532nm | 6 ns | 800mJ | 1 to 7mm continuously adjustable | 1 to 10 Hz | Electro-optic Q-switch, 7-joint arm, water and air cooling |
Convert to fluence before comparing. QN-03 at its 400mJ ceiling gives roughly 3.2 J/cm² at a 4mm spot, 12.7 J/cm² at 2mm. QN-12 at 800mJ delivers around 8.9 J/cm² through the 3x3mm square. QE-01 at 800mJ sits near 6.4 J/cm² at 4mm, 2.1 J/cm² wide open at 7mm. Conversions of published maxima, not settings.
QE-01 has the widest spot range and fastest repetition rate, so it covers a broad shoulder patch quickly. QN-12's homogeneous beam spreads energy evenly instead of peaking in the centre. QN-03 adds multi-pulse stacking at a lower entry cost. Compare the range on the Q-switched Nd:YAG laser page, then request the 1064nm spec sheet or a call with an application engineer. Our guide to nevus of Ota laser treatment transfers almost directly, and the Ota solution page covers the face.
What to check before you buy
Wavelength is the easy part. These questions decide whether the machine earns money in year three.
- Certification. Pmise equipment is certified under FDA, CE, RoHS and SGS. Ask which certificate covers your exact model, then check your own regulator's rules.
- Training. Technical instructors train your team after purchase at no charge. Operator skill, not the laser, keeps complications low.
- Warranty. One year from receipt and acceptance, free repair of the whole unit against invoice and warranty card, artificial damage excepted.
- Maintenance. Lifetime maintenance on all Pmise laser equipment, with a worked-out solution for consumables or repair.
- Consumables. Running costs are the flashlamp, the optics and the tips. Get service life and unit price before you sign.
- Support. Technical consulting answered inside 30 minutes, a quotation in 12 to 24 hours, a full solution in 24 to 72.
- Lead time. This shifts with model and destination. Ask for a written delivery date, not a catalogue figure.
Ready to move? Send your case mix and ask for a quotation or a demonstration. Distributors can raise territory terms with the same team.
Aftercare and precautions
Shoulders rub against straps, backpacks and seatbelts, so aftercare advice has to be specific.
- Keep the area clean and dry, and let crusts separate on their own. Picking scars.
- Use broad-spectrum sun protection, or cover the site, for weeks after each pass.
- Avoid friction from straps and tight clothing while the skin heals.
- Counsel darker skin types on post-inflammatory hyperpigmentation beforehand.
- Respect the interval. Treating too early stacks inflammation and raises pigment risk.
- Escalate blistering, prolonged redness or scarring to the treating clinician.
Our archive is realistic about risk: in experienced hands and with capable equipment, complications on dermal melanocytic lesions are exceedingly rare, though inflammatory hyperpigmentation and occasional scarring do happen. Conservative fluence, cooling, a test spot and careful selection keep them low.
Educational note: this page supports equipment evaluation and clinical planning. It does not replace a clinician's diagnosis, assessment or treatment decisions.
Frequently Asked Questions
How is nevus of Ito different from nevus of Ota?
Same disease process, different address. Both are dermal melanocytosis: melanin-rich melanocytes trapped in the dermis. Nevus of Ota follows the trigeminal nerve and can involve the eye. Ito sits in the shoulder girdle. Histology, laser approach and complication profile are near identical, so one 1064nm platform treats both.
How many sessions will a patient need?
No fixed number, and you should resist giving one. Most patients need several sessions spaced weeks to months apart, since the lymphatic system clears shattered pigment slowly. Larger, darker, deeper lesions take longer. Assess the lesion, run a test spot, then set expectations from what you see.
Is treatment safe on darker skin?
The 1064nm Q-switched Nd:YAG is the gentlest pigment wavelength for higher Fitzpatrick types, since epidermal melanin absorbs it weakly. Risk isn't zero. Post-inflammatory hyperpigmentation is likelier in darker skin, so use conservative fluence, cool the epidermis, stretch the interval between sessions and insist on sun protection.
Recommended Equipment
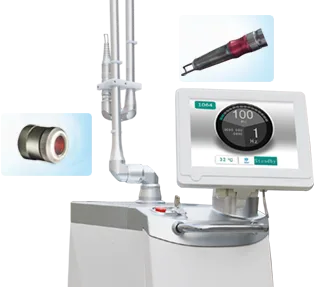
Pmise QE-01
Dual wavelengths (1064nm & 532nm) are convenient to adjust by touching LCD. Multi-spot size (1-7mm) is ideal for a wide…
View details
Pmise QE-02
Dual wavelengths (1064nm & 532nm) are convenient to adjust by touching LCD. Multi-spot size (1-7mm) is ideal for a wide…
View details
Pmise QN-05
Patented technology of single lamp and dual rods doubles energy output (400mj). Shorter pulse width (6-8ns) than ordina…
View details