Ablative vs non-ablative laser resurfacing comes down to one trade. An ablative device removes tissue, so the change is bigger and arrives faster, but the patient pays for it in recovery days. A non-ablative device only heats the dermis, so the skin stays intact and the result builds slowly. Which one belongs in your clinic depends on who walks through your door.
Both families can be delivered fractionally. That's the part buyers most often get muddled, so let's start there.
What actually separates ablative from non-ablative?
The dividing line is whether the skin surface survives the pass. Ablative lasers vaporize the outer layers. Non-ablative lasers leave the epidermis intact and put their heat underneath it. Fractional delivery is a separate idea layered on top of both: the beam gets split into a grid of microscopic columns, so treated tissue sits between untouched skin and healing runs much faster than a full-field burn. Manstein and colleagues described this fractional photothermolysis approach in Lasers in Surgery and Medicine in 2004, working with a 1.5 micron prototype. So a laser can be ablative and fractional, or non-ablative and fractional. The grid tells you nothing about whether the surface comes off.
What sets the mechanism is water. Skin is mostly water, and our engineering archive puts water's absorption peaks near 980nm, 1060nm, 1480nm and a strong one at 2940nm. A 10600nm CO2 beam is absorbed hard enough to boil tissue away on contact. A 1550nm beam is absorbed more gently, so it drives heat into dermal micro-columns without breaking the barrier. Same fractional grid, completely different wound.
Ablative equals surface removed, stronger result, longer recovery. Non-ablative equals surface preserved, gentler result, minimal recovery. Everything else is detail.

Ablative fractional CO2 at 10600nm: the heavy-correction option
Fractional co2 is the strongest resurfacing service most clinics will ever offer. Each focal spot dumps enough energy to ablate a micro-channel slightly wider than the spot itself, and around that channel sits a ring of coagulated tissue plus a wider zone of simple heating. Our device manuals note that pulse width steers that ring directly: shorter pulses leave less coagulated tissue behind, longer pulses leave more. Depth of ablation isn't a single number either. It shifts with wavelength, how much water the tissue holds, how many passes you run, and the fluence you dial in.
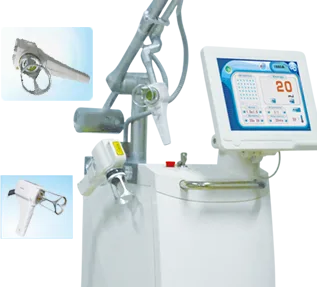
That adjustability is why ablative CO2 carries the broadest indication list. On the Pmise CF-01 ultrapulse CO2 fractional laser the operator can pick continuous, ultra-pulse or fractional output, run pulse durations from 0.067ms to 6.7ms, and change spot density between 6x6, 12x12 and 24x24 spots per square centimetre across 1x1, 2x2 and 3x3cm scan areas. Three lens options ship as standard: a fixed-focal cone for the deepest work, an adjustable-focal cone for shallow-to-deep peeling on the fly, and a roller-type cone made for the orbital area, perioral zone and nose wings. Typical targets include:
- Atrophic, surgical and burn scars, including established acne scarring
- Deeper wrinkles, thinning skin and photoaged laxity
- Stretch marks and general texture reconstruction
- Warts, small benign growths and epidermal pigmented lesions
Our technical documentation describes the sealed radio-frequency excited CO2 source as holding output more consistently over its service life than a sealed glass tube, which matters if you're running a busy list day after day. The price of all this power is recovery. Ablative work means days of redness, oozing and crusting, and it demands real caution in higher-melanin skin where post-inflammatory hyperpigmentation is a live risk. Train your operators properly or don't buy it. The clinical workflow sits on our ablative skin reconstruction page.
Non-ablative 1550nm: minimal downtime, more visits
The 1550nm erbium glass fractional laser is the gentle end of skin resurfacing, and it sells to a completely different patient. There's no open wound, because the beam heats micro-columns in the dermis while the barrier stays shut. Alexiades-Armenakas, Dover and Arndt, reviewing the field in the Journal of the American Academy of Dermatology in 2008, put it plainly: non-ablative resurfacing creates dermal thermal injury while preserving the epidermis, and these intermediate techniques traded some of the ablative result for lower risk and shorter recovery.
Here's a number worth quoting to a hesitant patient. On the Pmise EF-01 erbium glass fractional laser, treated-surface coverage runs roughly 1.56% at 36 spots per square centimetre, about 6.25% at 144 spots, and around 25% at 576 spots. Even at the densest setting three quarters of the skin is never touched. That is the whole reason recovery is short. Our device manuals also note that fractional mode is generally well tolerated with topical anaesthesia alone, and that post-treatment care is far simpler than full-field work.
Common indications:
- Photoaging, fine lines and early wrinkles
- Atrophic scars and acne scarring
- Enlarged pores, rough texture and mild laxity
- Stretch marks and general facial rejuvenation
The catch is arithmetic. Gentler passes mean a series of appointments before anyone sees the change they were promised, and collagen remodelling is gradual by nature. Set that expectation at consultation, not at session three. More on the treatment logic in our non-ablative skin resurfacing solution.
Downtime against result: the comparison table
Read the rows below as tendencies, not guarantees. Settings, operator technique and skin type move every one of them.
| Attribute | Ablative fractional CO2 (10600nm) | Non-ablative 1550nm |
|---|---|---|
| Skin surface | Vaporized | Preserved |
| Water absorption | Strong | Moderate |
| Residual heat and tightening | Highest | Moderate, contained in columns |
| Best for | Deep scars, deep wrinkles, laxity | Fine lines, early aging, maintenance |
| Result per session | Highest | Gradual, builds over a course |
| Relative downtime | Longest, measured in days | Shortest, close to none |
| Sessions usually needed | Fewer | Several |
| Higher-melanin skin | More caution required | Generally easier to manage |
| Anaesthesia | Heavier requirement | Often topical only |
Which patients fit which treatment?
Match the platform to your patient base, not to the spec sheet you liked best. Four questions settle it:
- What are people actually asking you for? Deep scar revision and serious wrinkle correction point at ablative CO2. Refresh, glow and fine lines point at 1550nm.
- How much downtime will they tolerate? A lawyer with client meetings all week won't accept crusting. A patient who's saved for one big correction often will.
- How many visits will they book? Non-ablative needs a course. Ablative usually needs fewer sessions at a higher ticket. Both models work; they just fill your diary differently.
- What skin types dominate your market? In predominantly darker-skinned populations, conservative settings and strong operator training aren't optional. Non-ablative protocols tend to be the safer starting point.
Wondering where Er:YAG fits between these two? Our full fractional wavelength comparison covers it.
One platform, both, or a dual-mode machine?
Plenty of clinics end up running both ends of the spectrum, and that's usually the right call, because the two services sell to different people. Ablative wins the high-value correction cases. Non-ablative fills the calendar with downtime-averse regulars who come back. Neither cannibalises the other.
If cash flow forces one purchase, choose by inquiry mix. Scar and deep-wrinkle enquiries dominating? Buy ablative. Market full of professionals who want to look rested by Monday? Buy 1550nm. There's also a middle path: the Pmise DF-01 dual-mode fractional laser combines 1550nm erbium and CO2 fractional delivery in one console, which suits a clinic that wants both service lines without two footprints and two service contracts. Floor space is expensive. This matters more than the sticker price.
What to verify before you order
Clinical fit is half the decision. The rest decides whether the machine is legally sellable and practically serviceable where you are.
- Certification: CE marking for the EU, ISO 13485 for the factory, plus whatever your national regulator requires, such as FDA 510(k) status for the US. Ask for certificate numbers and scope, not a logo on a brochure.
- MOQ and lead time: confirm whether single-unit orders are accepted and get production plus shipping time in writing.
- Warranty and spares: check the term on the laser source and handpieces, expected source lifetime, availability of consumable tips, and how support works across your time zone.
- Running cost: a stable source that holds its output saves you more over five years than a cheap purchase price ever will.
Pmise supplies compliance documentation and full spec sheets on request. Tell us your target market when you request a quote so we can confirm the right certification package, and ask for a demo before you scale an order.
Frequently Asked Questions
Is ablative or non-ablative better for acne scars?
Both work, at different depths. Ablative fractional CO2 removes tissue and adds collagen-stimulating heat, which suits deeper, established atrophic scarring, and the patient accepts real recovery time in exchange. Non-ablative 1550nm treats more gently across a series of visits, a better fit for shallower scars or anyone who can't disappear for a week. Clinics that own both simply choose per case at consultation.
How much downtime does non-ablative resurfacing really need?
Much less than ablative, since the surface is never removed. Expect redness and mild swelling that settle quickly rather than the days of crusting an ablative pass produces. Don't oversell it as zero, though. The honest framing for patients is minimal social downtime traded against needing several sessions before the result looks finished.
Why does ablative give a stronger result in one session?
Two effects stack. The beam vaporizes columns of tissue, and the coagulated ring around each column adds thermal stimulus for remodelling. A non-ablative device only delivers the second half of that. More injury per pass means more change per pass, which is also exactly why recovery is longer and why settings need care in darker skin.
Can one machine do both?
Yes. Dual-mode fractional platforms carry a 1550nm erbium source and a CO2 source in a single console, so you can run a gentle maintenance list and a heavy correction case on the same day without buying two systems. It costs more than a single-wavelength device and less than two. For a clinic testing demand for both services, it's often the sensible first purchase.
Written by the Pmise Technical Team. Pmise builds laser and light-based aesthetic systems, including ablative CO2 and non-ablative 1550nm fractional platforms, and exports to clinics and distributors worldwide. This article draws on our own device documentation and the published laser-dermatology sources cited above. Always confirm treatment protocols and safety settings with a qualified physician.