

Seborrheic keratosis removal comes down to controlled ablation: you vaporize the raised, benign growth in thin passes and stop the moment you reach normal skin. Two wavelengths do most of this work, CO2 at 10600nm and Er:YAG at 2940nm. Both take the lesion off. They differ in how much heat lands underneath, and that drives bleeding, healing time, and how easily you overshoot.
What exactly is a seborrheic keratosis?
It's a benign epidermal growth that never has to be treated. Lesions look waxy and "stuck-on", usually brown or tan, and they sit proud of the skin instead of sinking into it. The StatPearls review on seborrheic keratosis describes them as immature epidermal keratinocytes and notes they become more common with age, affecting almost all adults aged 60 and over. Older patients rarely arrive with just one. Because the growth sits in the epidermis, it's a near-perfect target for surface ablation.
Treatment is elective. The American Academy of Dermatology is blunt about that: these growths are harmless, so most need no treatment. Patients ask anyway, over looks or a lesion under a bra strap that keeps catching.
When do you biopsy before you touch the laser?
Biopsy anything you're not certain about. Ablation destroys the tissue, so it destroys the only material a pathologist could have examined. The AAD says the same from the diagnostic side: a growth that might be skin cancer gets shaved off and read under a microscope. Stop signals, not lesions to vaporize:
- Rapid or recent change in size, shape, or color
- Irregular, pearly, or poorly defined borders
- Ulceration, bleeding, or a surface that won't heal
- Fine visible vessels running through the lesion
- One lesion that looks nothing like the patient's others
That last check, the ugly duckling, catches more than any other. A biopsy costs a week. Vaporizing a melanoma costs far more.
Who should you not treat, or treat with extra caution?
Diagnosis isn't the only reason to stop. Plenty of patients with an unmistakably benign keratosis are still poor candidates on the day, and an elective procedure gives you every reason to wait. These are general practice points; your device manual and local scope of practice come first.
- Active infection at the site, or cold sores in the history there. Ablation strips the barrier and can wake up herpes simplex around the lips. Postpone, and handle antiviral cover as your protocols require.
- Keloids or hypertrophic scarring in the history. This patient can end up with a worse mark than the growth you removed. One small lesion first, shallow, and be willing to decline.
- Recent isotretinoin. Healing after ablative procedures is a long-standing concern with this drug. Defer, and follow the interval your device manual and local guidance give rather than a forum post.
- Bleeding tendency or anticoagulant therapy. Oozing hides the base, and the base is what you're judging. Coordinate with the prescribing physician, favour the wavelength that coagulates as it cuts.
- Fitzpatrick IV to VI skin. The realistic risk here is pigment change, not scarring. Test spot somewhere discreet, see how the pigment settles, then treat the rest at conservative depth.
- Pregnancy. Nothing here is urgent. Reschedule.
- Room safety, before anything fires. Run smoke evacuation with the nozzle close to the site. NIOSH warns that plume from laser and electrosurgical procedures can carry toxic gases, bioaerosols and cellular material, and that room ventilation alone won't capture it at the source. Everyone present wears eyewear rated for the wavelength, and the patient gets shields.
CO2 vs Er:YAG for seborrheic keratosis: which one, when?
Heat the water inside tissue fast enough and it flashes to vapor, carrying the cells with it. That's ablation in one sentence, and the principle goes back to Anderson and Parrish, who laid out selective photothermolysis in Science in 1983. Water is the chromophore for both wavelengths, but Er:YAG at 2940nm sits closer to its absorption peak, so the energy is swallowed in a very thin layer. CO2 at 10600nm reaches further and leaves thermal effect below the crater. That residual heat isn't a flaw: it coagulates small vessels and keeps the field dry.
| Factor | CO2 (10600nm) | Er:YAG (2940nm) |
|---|---|---|
| Water absorption | Lower, heat spreads wider | Higher, energy stays shallow |
| Ablation | Layered, coagulation margin | Precise, near-bloodless |
| Bleeding | Controlled by coagulation | Pinpoint bleeding likelier |
| Healing | Slower, redness lingers | Faster re-epithelialization |
| Best fit | Thick, broad or vascular plaques | Thin lesions, thin skin |
| Risk if overdone | Thermal injury, pigment change | Bleeding obscures the base |
Settings, handpiece and technique move every row above, so it's a framework, not a rulebook. High-volume clinics end up owning both. Our breakdown of CO2, Er:YAG and 1550nm fractional lasers covers the resurfacing side.
Controlling depth, pass by pass
Depth control is the whole job. Too shallow and the lesion is back in weeks. Too deep and an elective case turns into a scar. Reading a table is easy; choosing on a live patient is the step that gets skipped. Here's the rule of thumb for your operators.
Thin, flat, lightly raised lesions, and anything on the face, eyelid region or other thin skin, push you toward Er:YAG and the small-spot, low-energy end of your device's range: on our Er:YAG unit, a focusing tip near the 1mm end of its 1 to 6mm spot range. On our CO2 platform it means coming down toward the 50 micron end of the 50 to 2000 micron spot range, staying low in the 2 to 200mJ pulse energy band, and using the short end of the 0.067 to 0.67ms pulse width. Single pass, wipe, look again.
Thick, raised, broad-based or readily bleeding plaques push you the other way. Choose CO2, open the spot up so you cover the surface evenly instead of stippling it, and let the coagulation margin hold the field dry while you work down layer by layer. Three rules sit above all of it: test on one lesion first; wipe and re-read the base between passes; and take final parameters from the device manual and your own machine's output, never from an article.
- Confirm the benign diagnosis, then photograph the lesion.
- Clean the site, mark the border while the lesion is visible, anesthetize.
- Set spot size and energy by lesion thickness using the rules above.
- Run one pass, then wipe with saline gauze to clear char.
- Inspect the base. Keratotic tissue looks and feels unlike dermis. Stop once it's gone.
- Feather the rim, then finish flat, dry and level with the surrounding skin.
The endpoint is what you see and feel, not a number on the screen. Chasing the last trace of pigment into the dermis is how these cases go wrong.
What does the hardware need to do?
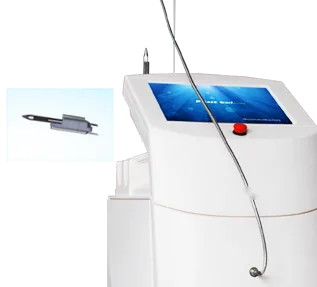
Precise lesion work asks two things of a machine: a spot you can size right down, and a pulse that repeats the same way every time. Our Ultrapulse CO2 fractional laser platform (10600nm) uses an RF-excited CO2 tube instead of a sealed glass tube, which our device documentation credits with more stable, more uniform output over a longer service life. Its specification lists continuous-wave, UltraPulse and fractional modes, the ranges quoted above, and a 7-joint articulated arm. Our 2940nm Er:YAG ablative fractional laser goes the other way, shallow by design: a 1 to 6mm adjustable spot with a 70 to 100 micron pixel focal spot, pulse widths from 200 microseconds to 2ms, interchangeable focusing and pixel tips, and listed applications including epidermal pigmented lesions and removal of abnormal skin growths.
Specs decide whether a machine can do the job, not whether buying it is a sound commercial move. Clinic owner or distributor, get these in writing from any supplier, us included:
- Certification for your market. Our company profile lists CE, FDA, RoHS and SGS certification. Ask for the document set covering the exact model and your importing country, and read it before the order goes in.
- Training and ramp-up. Technique-led work, so a device nobody trusts earns nothing. Pmise sends technical instructors to train your team after purchase, with continuing phone support, as our service and support page sets out.
- Warranty and after-sales response. That page also covers warranty terms, lifetime maintenance and published response windows. Response speed matters more than sticker price when a booked-out clinic has a dark machine.
- Consumables and spare parts. Tips, handpieces and arm optics wear. Confirm what's stocked and how replacements are handled long term.
- Distribution and branding terms. Reselling rather than operating? Ask about territory, branding options and demo unit support. Our network reaches clinics in more than 160 countries and regions, with terms agreed case by case.
Want a specification sheet or a quotation for either the 10600nm CO2 platform or the 2940nm Er:YAG unit? Talk to our team with your market, case volume and the lesions you see most. For protocol notes, see our seborrheic keratosis treatment page.
Healing and aftercare: what to tell the patient
Healing speed tracks the depth you reached far more than the laser you picked. The spot crusts over, and new epidermis grows underneath while the crust hangs on. Shallower Er:YAG work re-epithelializes sooner; deeper CO2 work stays pink longer. Promise an honest qualitative picture, not a number of days.
- Keep the site clean and moist with a bland ointment. Don't pick the crust.
- Expect pink skin at the spot, fading gradually.
- Sun protection is non-negotiable while the area heals.
- Come back if redness spreads, if there's pus, or if pain worsens.
Pigment change, not scarring, is the complication you'll actually meet, and it follows deeper ablation and richly pigmented skin. Our notes on Fitzpatrick skin types and laser settings go deeper.
Frequently Asked Questions
Is CO2 or Er:YAG better for seborrheic keratosis removal?
Neither wins outright. Er:YAG gives very shallow, precise ablation with minimal heat below it, which suits thin lesions and delicate sites. CO2 brings a coagulation margin that controls bleeding, so it handles thick or vascular plaques. Thickness, bleeding tendency and skin type decide it, and busy clinics keep both.
Will laser removal leave a scar?
Scarring risk stays low as long as ablation stays epidermal, because the lesion is superficial. Scars come from going too deep, or from stacking passes on one spot. Thin passes, a wipe between each one, and stopping at normal tissue keep you out of trouble. Pigment change is far more common.
Do treated lesions grow back?
A properly ablated keratosis rarely returns in the same place, since the growth is physically gone. But patients who form these lesions keep forming them, so new ones appear elsewhere over the years. That's new growth, not failed treatment. Say so before the first session.
Written by the Pmise Technical Team. Pmise manufactures laser and light-based aesthetic systems and supports clinics and distributors on device selection, parameters and operator training. This article is educational and does not replace clinical judgment.